
A heaviness or dragging sensation
In the vaginal area, often worse by the end of the day or after standing for long periods.
Heaviness
Women’s Health · Pelvic health · Lahore
A feeling of heaviness, pressure or a bulge in the vaginal area is often pelvic organ prolapse. It is common, it is not something to hide or put up with, and there are real, manageable options.
What is it?
Prolapse happens when the muscles and connective tissue supporting the bladder, womb or bowel weaken enough that one or more of these organs descends toward or into the vaginal wall. It is common, especially after childbirth or with menopause, and ranges from mild to more significant in how much it affects daily life.
For milder prolapse, pelvic floor physiotherapy alone is often enough to reduce symptoms meaningfully. More significant prolapse may need added support, and where surgery should be discussed we refer you to the right specialist alongside conservative options.
What you may notice
In the vaginal area, often worse by the end of the day or after standing for long periods.
HeavinessAt or near the vaginal opening, sometimes more noticeable with straining.
A bulgeThat eases when lying down.
On your feetSometimes needing to change position to fully empty.
EmptyingRelated to the sensation of pressure or the prolapse itself.
IntimacyWhich are the two most common times prolapse becomes noticeable.
Life stageSCROLL FOR THE ASSESSMENT TO FIND YOUR ROOT CAUSE
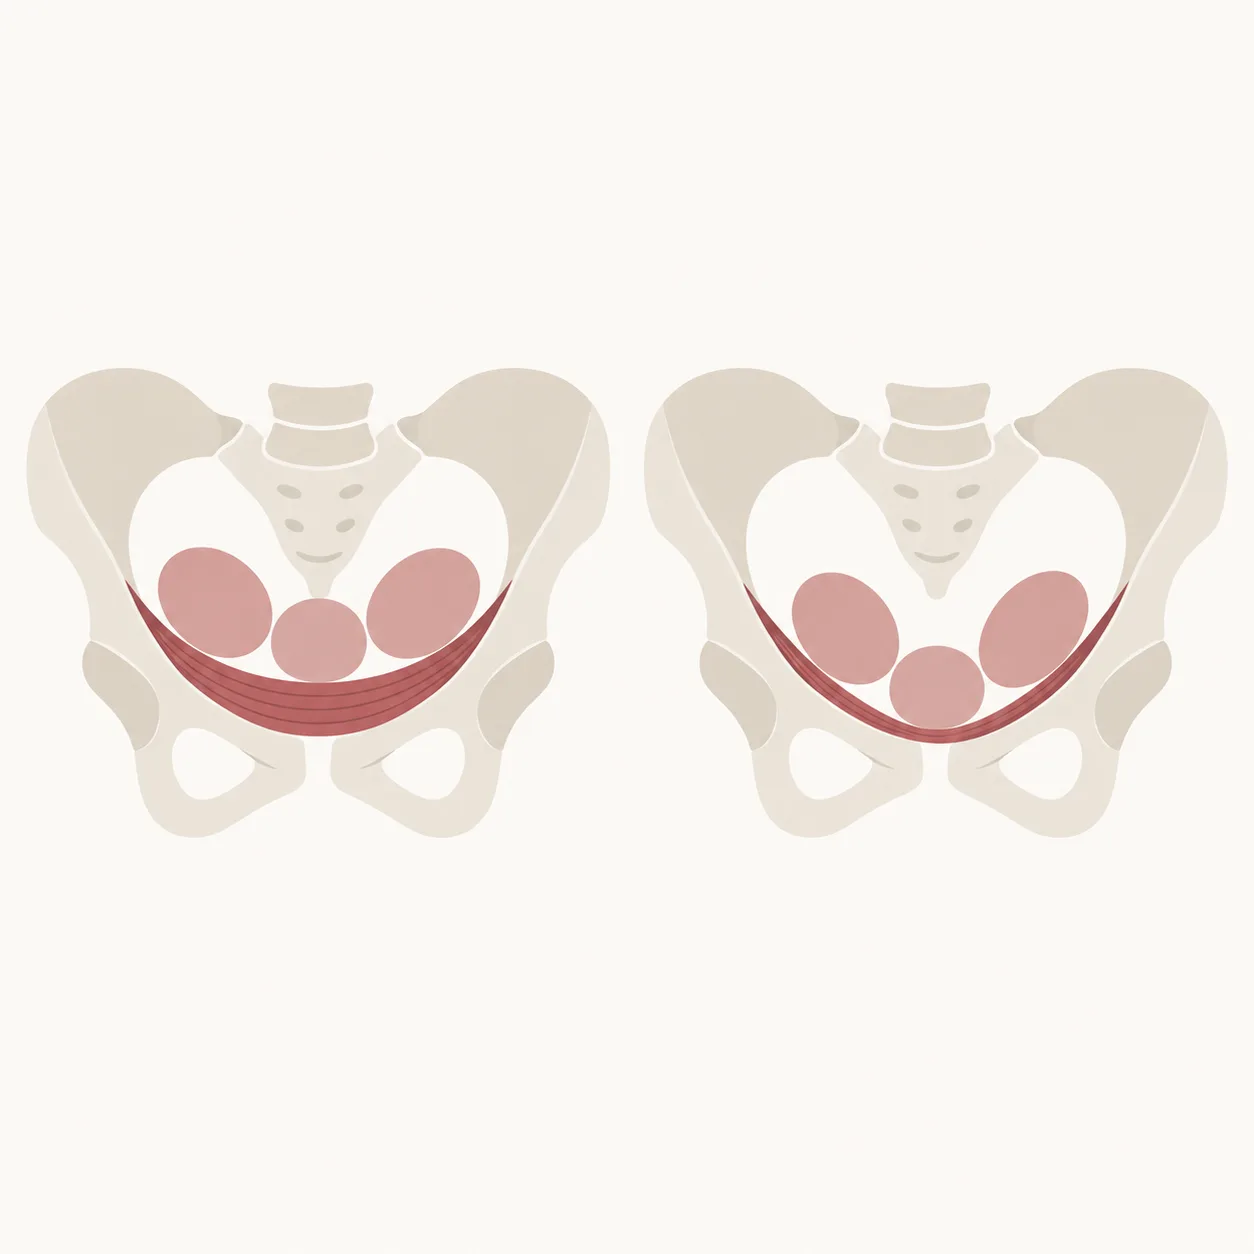
Understanding it
You do not need to have named this as “prolapse” before getting in touch. Many women describe it as a heaviness or pressure long before knowing what it is, and an assessment tells you exactly what is happening and what your options are.
These symptoms are genuinely common, and not something to hide or endure.
How much it affects daily life varies, and so does the support that helps.
For milder prolapse, pelvic floor physiotherapy alone is often enough to reduce symptoms.
Our advanced treatment techniques
There is no single answer for every prolapse. An assessment works out where you are, and your plan is built from there.
Pelvic floor physiotherapy alone is often enough to reduce symptoms meaningfully.
Where symptoms remain despite strengthening work, added mechanical support can hold the organs in a better position while you continue physiotherapy.
Where prolapse is significant or surgical options should be discussed, we refer you to the right specialist alongside conservative options.
Examples at home
Slow, low-effort movements that keep pressure off the pelvic floor. Which of them helps depends on your assessment.

Learn to breathe out as you start a movement, rather than holding your breath and bearing down.

A comfortable position that takes the weight off the pelvic floor.

Coordinate the breath, the deep core and the hips without strain.

A resting position that lets the pelvic floor and lower back let go.
These are examples of what an assessment may build into a plan, not a programme to start on your own. Stop if anything hurts or you feel more pressure or heaviness afterwards.
Step by step
First 15 minutes. Your symptoms, your birth and medical history, and what you are hoping physiotherapy can help with.

30 to 40 minutes. With your informed consent at every step, we assess the type and degree of prolapse and what support suits you. External-only assessment is always available if you prefer.

A programme to strengthen and coordinate the muscles that support your pelvic organs, matched to what your assessment found.

Where prolapse is significant or surgical options should be discussed, we refer you to the right specialist alongside conservative options.

Your first visit
Appointments are one-to-one with a female physiotherapist in a private, women-only studio. You will leave your first session with a clear picture of your prolapse and what can help.
Any examination is explained beforehand and requires your explicit agreement. You remain in control throughout.
You can pause or stop a session at any point, or ask for an external-only approach instead.
Where prolapse is significant or surgical options should be discussed, we refer you to the right specialist.
Questions
No. It is common after childbirth at any age, and menopause is a separate, additional time it can become more noticeable due to tissue changes.
For milder prolapse, pelvic floor physiotherapy alone is often enough to reduce symptoms meaningfully. An assessment tells you how much support your pelvic floor needs and what is most likely to help.
Not necessarily. Conservative management is often tried first. Where prolapse is more significant, we will discuss referral honestly as an option alongside it.
No examination is automatic or mandatory. It may be recommended where it will genuinely help, but it is always explained first, separately consented to, and you can decline it and still be assessed and treated through external methods.
Pessary support is coming soon, with Dr Munaza Ghani, who is MSOMPT-qualified in pelvic health. Ask us directly and we will tell you where it stands and whether it could suit you.
The studio is a private, home-based space in Hasham Street, Karim Block, Allama Iqbal Town, Lahore. We share exact directions after booking, so your visit stays discreet.
Safety first
Your next step
You do not need a diagnosis, or the right words for what you are feeling. Tell us what you are noticing, and we will tell you honestly what your options are. Women-only · One-to-one · Your details stay between you and your clinician.