
A pop, or the knee shifting
Many people feel or hear a pop as the knee gives way during a cut, landing or sudden stop.
At the time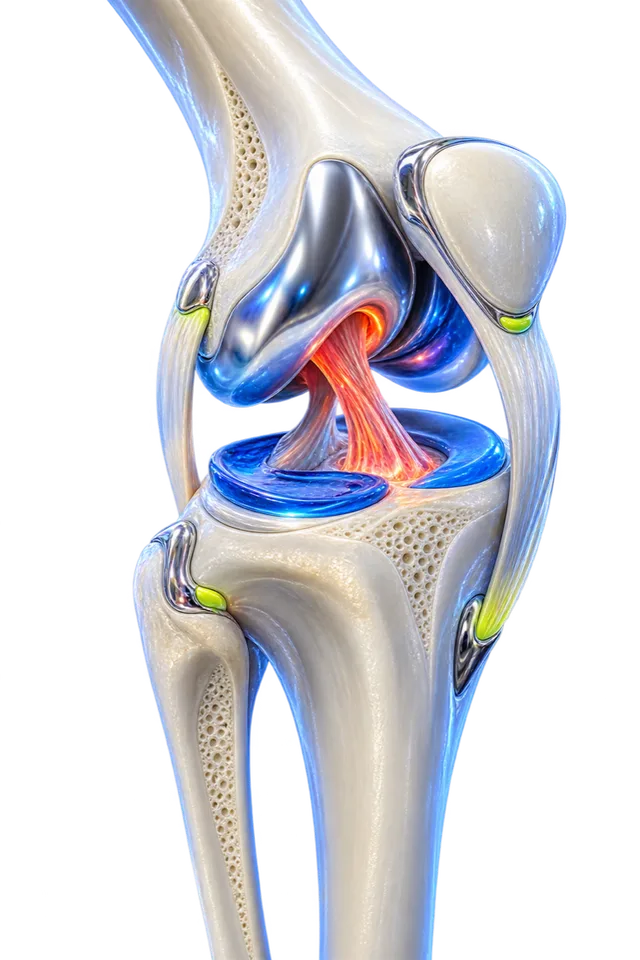
ACL Rehabilitation · Sports Physiotherapy · Lahore
An ACL injury is serious, but it does not have to end your sport. The research is clear: the quality of your rehabilitation, and not just the surgery, is the biggest predictor of your outcome, and the phase most people rush is the return to sport. Private physiotherapy with a female physiotherapist in Lahore, before surgery, after it or years later.
The short answer
The anterior cruciate ligament (ACL) is a strong band inside the knee that joins the thigh bone to the shin bone. It stops the shin sliding forward and keeps the knee stable when you cut, pivot and land. When it tears, you may feel a pop, the knee swells within hours, and it gives way or does not feel trustworthy.
Rehabilitation, with or without surgery, restores movement, rebuilds strength and control, and tests you against objective criteria before you return to sport. It starts before surgery, follows your surgeon’s protocol after it, and progresses by what your knee can do, not by the calendar.
At a glance
The figures that shape a good plan, from published research. Your own assessment sets your timeline.
Relative ACL injury risk in female against male athletes, depending on the sport (Voskanian, AJSM).
The usual time from reconstruction to a tested return to sport.
The strength and hop-test target against the other leg before going back.
Reported fall in ACL tears in footballers who did a season of structured neuromuscular training.
What you may notice
Many people feel or hear a pop as the knee gives way during a cut, landing or sudden stop.
At the timeThe knee swells within hours because the ligament has a rich blood supply.
Hours laterIt buckles on turning, on stairs or when you change direction.
Giving wayIt will not fully straighten or bend. A locked knee can mean a torn meniscus as well.
MovementYou walk with a straight, careful knee and avoid the stairs.
WalkingMonths after injury or surgery you still avoid running, jumping or sport, or you doubt your knee.
Months onSCROLL FOR THE ASSESSMENT TO FIND YOUR ROOT CAUSE
ACL or something else?
Several problems cause knee pain, and they are treated differently. These patterns help tell them apart; they cannot diagnose you, and the ACL often comes with meniscus or cartilage injury.
Only an examination, and sometimes an MRI, tells these apart. A locked knee, or a knee that will not take weight, needs a doctor promptly.
Inside the knee
Pick a step to see it in a woman’s knee from the front. These describe terms you may hear; they are not a checklist for diagnosing yourself.
A strong band inside the knee that runs from the inner wall of the outer thigh-bone condyle down and across to the front of the shin bone, crossing the posterior cruciate behind it like an X. It stops the shin sliding forward and steadies the knee when you pivot.
Most ACL tears happen without contact: decelerating, cutting or landing with the foot planted while the knee collapses inward (dynamic knee valgus). The thigh drops in over the shin, the ligament is stretched past its limit and gives, often with a pop.
From puberty the female pelvis is proportionally wider, so the thigh angles in more towards the knee, and a knee that is already angled collapses inward more easily. The notch the ACL passes through is often narrower, and hormones soften connective tissue.
A torn ACL does not heal on its own. When surgery is chosen, the surgeon replaces it with a graft, commonly a hamstring tendon, the middle of the patellar tendon or the quadriceps tendon, threaded through a tunnel in each bone. The graft needs months of loading to mature.
The hamstrings pull the shin back and the quadriceps and hip muscles control the thigh above. Strong, well-timed muscles share the load and protect the ligament or its graft. Retraining them, and how you land, is the heart of rehabilitation and prevention.
A teaching drawing, not your knee. Which structures are hurt, and how stable the knee is, are found at your examination and, where needed, on an MRI.
Inside the knee in 3D
The 3D model of a woman’s knee and leg follows each point as you read: the ACL and PCL crossing in the notch, the thigh dropping in over the shin as the ligament stretches and gives, the angle a wider pelvis gives the thigh, and the graft that replaces a torn ligament with the muscles that guard it.
The ACL runs from the outer thigh-bone condyle to the front of the shin bone, crossing the PCL like an X. Your examination tests how much the shin slides forward and how the knee turns.
Landing or cutting with the foot planted while the thigh drops in over the shin stretches the ligament past its limit. That inward collapse, dynamic valgus, is also what we retrain.
A wider pelvis angles the thigh in more, so the knee starts closer to collapse. Add a narrower notch, softer tissue and quadriceps-dominant landing, and the risk climbs, but the movement part can change.
A reconstruction uses a tendon graft through a tunnel in each bone. It needs months to mature, and strong hamstrings, quadriceps and hip muscles protect it while it does.
Why women are at higher risk
This is physiology, not a failure of effort, and it is well studied. Some of it is fixed; the part you can train is the part that matters most.
Hormones and anatomy are not things to fix. Movement is: that is what prevention and rehabilitation work on.
The first decision
Not every ACL injury needs reconstruction. The choice depends on your sport, how much the knee gives way, other injuries and your goals, and it is made with your orthopaedic surgeon.
Many people who start with rehab still go on to surgery, and that is fine: the work you did beforehand is not wasted.
How it is assessed
Your history and a hands-on examination come first. Scans and tests are used when they change what we do.
An MRI is used to look at the meniscus, cartilage and the ligaments when the picture is unclear or when surgery is being considered.
Myths and facts
A few common beliefs lead people to rush, or to give up. These are the ones we hear most.
None of this means your worry is wrong. It means there is a clear, honest way forward.
Recovery in phases
Each phase has goals that must be met before the next begins. The timeframes are typical after reconstruction, not a calendar.
Protect the repair, get the knee straight, wake the quadriceps, control swelling, and walk with crutches as directed.
Progressive weight-bearing, closed-chain exercise, hip and core work, normal walking and first balance training.
Progressive resistance for quadriceps, hamstrings, glutes and calf, with single-leg work and balance on unstable surfaces.
Jumping, landing and hopping with attention to knee collapse, a running progression and strength testing.
Drills at game intensity, change of direction and decisions under fatigue, the phase most programmes skip.
Hop tests, strength, movement quality under fatigue and confidence, all passed before you go back.
Before surgery, the aim is a calm, straight, strong knee. After it, you also follow your surgeon’s protocol and restrictions.
Before you go back
Evidence suggests at least 90 per cent limb symmetry on strength and hop tests before returning. Many people return at 70 to 80 per cent and re-injure more often. This is what we test.
Single, triple, crossover and six-metre timed hops, each against the other leg.
A repeated single-leg sit-to-stand for quadriceps endurance after reconstruction.
Screens for knee collapse on landing, the fault linked to first and repeat ACL injury.
Quadriceps and hamstring strength against the other leg and against each other.
Landing control reassessed when tired, since many re-injuries happen late in a game.
Trust in the knee and fear of re-injury, asked about directly. A knee you do not trust is not ready.
In one study, athletes who passed a full set of criteria had far fewer re-injuries than those who did not (Grindem, BJSM 2016).
ACL exercises at home
Examples of early work used before and after surgery. Which of them suits you, and when to move on, depends on your assessment and your surgeon’s protocol; after surgery, do only what your surgeon and physiotherapist have agreed.

Wake up the thigh muscle that switches off after injury or surgery.

Regain bending of the knee within the range your surgeon allows.

Build control of the quadriceps without bending the knee under load.

Strengthen the hamstrings and glutes that protect the knee.

Practise bending and straightening both knees with the knees tracking over the toes.

Retrain the knee’s sense of position and the hip muscles that steady it.
Stop and ask for advice if the knee swells, locks, gives way or the pain climbs, or if a calf becomes hot, swollen and tender.
Day to day
Small daily habits calm the swelling and protect the knee while it heals.
Getting the knee fully straight early matters. Rest with it supported straight, not propped on a pillow under the knee.
Elevate the leg above the heart, use cold for short spells wrapped in a cloth, and keep walking little and often.
Use your crutches as directed and aim for an even, heel-to-toe walk as soon as you are allowed, rather than limping.
Five minutes of quad sets and heel slides several times a day beats one long session.
Protein, enough sleep and keeping up your other fitness support healing and the rest of your training.
Worry about the knee is common and normal. Say so; it is part of the plan and part of the return-to-sport tests.
Pain relief and any brace are matters for your doctor, surgeon and physiotherapist.
Step by step
How the injury happened, whether you have had surgery, your sport and goals, your surgeon’s protocol, and any worry about the knee.
Safety checks first, then the knee, your range, strength and control, how you walk, balance and land. Every step is explained and nothing is forced.
What is likely hurt, what is not, whether you need an MRI or your surgeon first, and what rehab can and cannot do.
Your first exercises, how much, how often and when to move on, with criteria for each phase, and coordination with your surgeon with your consent.
Care designed for women
Munaza Physio Studio is a women-only physiotherapy practice. Your knee is assessed one-to-one by a female physiotherapist in a private room, with hands-on manual therapy as well as progressive loading, so you can describe your sport, your cycle and your worries without hesitation.
Women-only environment with a female physiotherapist
A private room for assessment and treatment
One-to-one sessions, never a shared slot, never rushed
The female athlete understood: anatomy, hormones and movement
Home visits across Lahore when getting out is hard

Real Stories
My mother had a stroke that left her right arm and leg immobile. With Dr. Munaza’s expert physiotherapy, she regained full movement completely painfree and without any medication. We’re truly grateful for her care and professionalism.
I took home sessions for my neck, shoulder, back, and hip pain. Alhamdulillah, all my pain is gone like a magic. Even my headache, which I had for many years, got better with the exercises. Thank you so much Dr Munaza for your kind treatment and care. May Allah bless you.
“Dr. Munaza treated my neck and shoulder pain, as well as my muscle pull issue, very effectively. With the help of exercises and therapy, I feel much better now. She is very kind, caring, and cooperative. Highly recommended!”
I had neck pain with headaches for a long time. After treatment with Dr. Munaza, my pain got much better and the headaches eased. She listened carefully, treated me gently, and explained everything clearly. I feel relaxed and thankful for her care Best physiotherpist in the area👍🏻
Dr. Munaza is very kind and professional. My shoulder pain improved within a few sessions. Highly recommended!!!!
Simple pricing
Transparent pricing, with a personalised assessment at the start of every plan.
Clinic sessions start from PKR 1,500.
Home visit pricing depends on your location and condition, contact us for a quote.
Book AssessmentA knee you can trust
An ACL injury is a long road, and it is one you can walk well. The aim is a knee you trust in your sport, strength and landing that protect it, and a return that is earned by criteria and not rushed by the calendar.
Questions
The anterior cruciate ligament (ACL) is a strong band inside the knee that joins the thigh bone to the shin bone. It stops the shin sliding forward on the thigh and gives the knee rotational stability when you cut, pivot, land or change direction.
Typically a pop or a feeling of the knee shifting at the moment of injury, swelling within hours, pain, and a knee that gives way or does not feel trustworthy afterwards. Only an examination, and sometimes an MRI, confirms it, and other structures such as the meniscus are often hurt at the same time. Get it examined soon after the injury rather than walking it off.
No. In a randomised trial (Frobell, NEJM 2010), young active adults who started structured rehabilitation and had surgery only if they still needed it did as well at two and five years as those who had reconstruction straight away. Surgery is more likely to be advised if you play pivoting sports, the knee keeps giving way, or other structures are damaged. It is your decision with your orthopaedic surgeon; rehabilitation matters on either path.
The relative risk is roughly three to eight times higher in female athletes, depending on the sport (Voskanian, American Journal of Sports Medicine). A wider pelvis angles the thigh in towards the knee, the notch the ligament passes through tends to be narrower, hormones such as relaxin soften connective tissue, and many women land and cut with the quadriceps doing more work than the hip muscles. The movement pattern is the part that can be retrained.
A typical timeline from reconstruction to tested return to sport is 9 to 12 months. Some people are ready at about 8 months, others need 14 to 16. In one cohort, each month return was delayed up to nine months cut the risk of re-injury by about half (Grindem, BJSM 2016), which is why we progress by criteria, not by the calendar.
Clearance usually means the graft has healed and the knee is stable. It does not mean you are ready for sport. Readiness is shown by strength, hop tests, movement quality under fatigue and confidence, and many people are medically cleared but not yet physically ready at six months. We test these objectively.
The evidence-based aim is at least 90 per cent of the other leg on quadriceps strength and on the hop-test battery, with good landing mechanics. Many people return at 70 to 80 per cent, and they re-injure more often. Passing a full set of return-to-sport criteria was associated with far lower re-injury in the Grindem study.
Most people return to some sport. A pooled analysis (Ardern, BJSM 2014) found roughly four in five returned to some sport, about two in three to their previous level and about half to competitive sport. Rehabilitation quality, strength and confidence all affect that, which is why the final phase and the testing matter.
Yes, in either knee. Roughly one in five young athletes who return to pivoting sport injure an ACL again (Wiggins, American Journal of Sports Medicine 2016). Returning too early, weak hamstrings and glutes, poor landing control and fatigue all raise the risk, and all of them can be trained.
Yes. Structured neuromuscular training that combines strength, balance, jumping and landing technique, done two to three times a week, lowers ACL injury rates. Programmes such as the PEP programme are reported to cut ACL tears substantially in footballers. We teach a version suited to your sport and age, and it also helps people who have had an ACL injury.
Yes, and both matter. Before surgery we calm the swelling, restore full straightening and bending, wake the quadriceps and normalise walking, because a calm, strong knee at the time of surgery recovers better. After surgery we follow your surgeon’s protocol and progress by criteria. We coordinate with your surgeon, with your written consent.
Not every ache after return to sport is the ACL. Later knee pain can be patellofemoral pain, iliotibial band syndrome or patellar tendon irritation (jumper’s knee), and stiffness or weakness can linger. A proper reassessment tells them apart and rebuilds your programme from where you are now, even years after surgery.
Yes. Munaza Physio Studio in Allama Iqbal Town, Lahore, is a women-only practice. Your assessment and rehabilitation are one-to-one with a female physiotherapist in a private room, at the studio or at home across Lahore, before surgery, after it or years later.
Safety first
Your next step
Tell us where you are, before surgery, after it or years out, what happened to your knee and what sport you want to get back to. We will tell you honestly how physiotherapy can help. Women-only · One-to-one · At the studio or at home in Lahore.
 5.0